Trip has spent nearly 30 years helping people find evidence to inform healthcare decisions. But having useful evidence in an index is only part of the challenge: users also need to be able to find it.
Traditional lexical search looks for matches between the words in a search and the words in documents. It works well in many situations, but it can struggle when a search is broad, when authors use different terminology, or when the same phrase has more than one meaning.
We have been exploring whether AI could help with these problems and also find important material beyond Trip’s index.
Starting with the user’s intention
Someone searching for “prostate cancer screening” might be interested in benefits and harms, screening tests, guidelines, or screening people at higher risk.
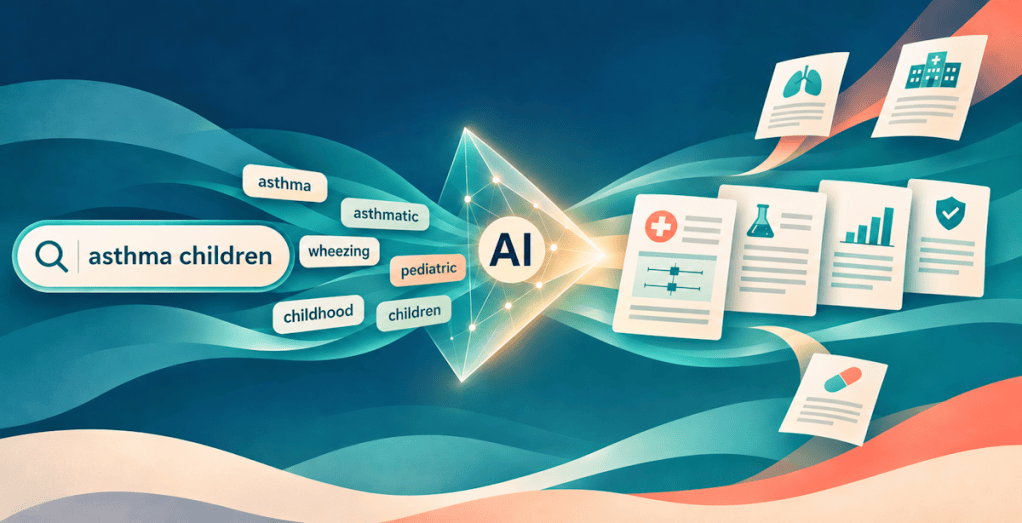
Similarly, a search for “asthma in children” could be about diagnosis, treatment, attacks, or triggers and risk factors.
One idea is to offer suggestions after the initial search, allowing the user to select the aspect they are interested in. Trip could then use that hint to run additional searches and reorganise the results.
What might happen behind the scenes?
Our experimental process has six steps:
- Run a broad search of Trip.
- Run one or more focused searches based on the user’s selected interest.
- Search for country-specific material, such as national guidance.
- Ask an AI system, such as ChatGPT with web search, to find additional relevant documents outside the results retrieved by Trip.
- Check those external discoveries against Trip’s full index, then combine and deduplicate the results.
- Use AI to rerank the combined list, taking account of relevance, evidence type, recency and local context.
The user would see one integrated list. Documents found externally that have no confident match in Trip’s index could be labelled “Beyond Trip” (as they are in AskTrip)
Example 1: prostate cancer screening
For this test, the initial search was “prostate cancer screening”, with a focus on people at increased risk. We imagined the user was a Canadian health professional, so Canadian guidance and policy were particularly relevant.
The broad search produced a strong first result: a Cochrane review of PSA screening. The narrower search also found relevant material, including a study of risk-adapted screening in a high-risk population.
But the narrower search showed the difficulty of interpreting “high risk”. Its third result was about treatment for already diagnosed high-risk prostate cancer, while its fourth concerned pancreatic cancer screening. Both contained matching words, but neither addressed the intended question.
The combined, reranked list brought forward Canadian guidance and research on screening people at increased risk. One particularly striking example was the IMPACT study of screening in BRCA1/BRCA2 carriers. It appeared at 54 in the broad search and 92 in the narrow search; in our illustrative reranking, it rose to fourth.
Knowing the user was in Canada also shaped the external search. It helped surface the Canadian Urological Association’s screening recommendations, a British Columbia government guideline and a Canadian review of screening in people at increased risk. These were presented alongside relevant international research.
Our external search also found a systematic review on family history, ethnicity and genetic risk. It wasn’t in either top-results export, but a check showed it was already in Trip – further down. That demonstrates why an external discovery should be checked against the whole index before being labelled “Beyond Trip”.
Example 2: asthma in children
For the second test, the search was “asthma in children”, with the user selecting “triggers and risk factors”. This time, we imagined a UK health professional.
The broad results included the BTS/NICE/SIGN asthma guideline, but the section ranked first concerned diagnosis in children under five. The focused search placed a NICE Clinical Knowledge Summary on risk factors and triggers second: a much closer fit to the chosen interest.
The focused search also found two recent systematic reviews of childhood asthma risk factors, but they appeared at positions 76 and 77. After combining and reranking the results, they appeared at sixth and fifth respectively.
The UK context helped the external search find NICE guidance on indoor air quality, NHS resources for professionals and government guidance on damp and mould. These sit alongside international research, including a systematic review of environmental exposures and asthma exacerbations in children. They have not yet been checked against Trip’s full index, so we cannot say which are genuinely beyond Trip.
In both examples, the country acted as a signal to look for locally useful material, not as a filter excluding evidence from elsewhere.
What happens next?
These are early, manually assisted examples, not evidence that an automated system will consistently perform better. The ranking involves judgement, and important questions remain about speed, reliability and how best to verify and deduplicate external discoveries.
The next step is to test the approach across a wider range of searches. We want to know not only whether the first page looks better, but also whether the process finds useful evidence that would otherwise have been buried or missed.
The aim is a search that combines Trip’s curated collection with AI-assisted discovery, while helping users find evidence that better matches what they actually wanted.





Recent Comments